
 570-630-9354
Alcohol-Related Dementia: Symptoms, Causes, and Treatment
Begin Today
Prolonged heavy alcohol use can contribute to alcohol-related brain damage and cognitive impairment. Alcohol-related dementia is not simply another name for Korsakoff syndrome. Thiamine deficiency can cause Wernicke encephalopathy, which requires urgent care. Abstinence and treatment may support partial recovery, but permanent impairment can occur.
Jump to Section
Memory problems, confusion, or changes in judgment can be frightening, especially when long-term heavy drinking may be involved. Alcohol-related dementia is a broad term used for cognitive problems linked to alcohol-related brain damage, but it is not the same as Wernicke encephalopathy or Korsakoff syndrome. Some people may improve with abstinence, nutrition, thiamine treatment, and ongoing medical care, while others may have lasting problems. If you are worried about yourself or someone close to you, a proper medical assessment matters because similar symptoms can have other causes. Treatment may also need to address alcohol use itself. For people seeking support through rehab Lake Ariel PA has, care should include both addiction treatment and careful attention to possible neurological and nutritional complications.
What Is Alcohol-Related Dementia?
Alcohol-related cognitive decline can affect memory, judgment, attention, and the ability to manage daily tasks after prolonged heavy drinking. This clinical label is still widely used, but clinicians may also describe the problem as alcohol-related brain damage (ARBD) or an alcohol-related neurocognitive disorder. These terms are not interchangeable with Wernicke encephalopathy or Korsakoff syndrome.
Alcohol may contribute to cognitive problems through several pathways, including direct brain effects, poor nutrition, thiamine deficiency, repeated withdrawal, liver disease, stroke, and head injury. Some people improve after they stop drinking and receive treatment, while others have lasting impairment. A medical assessment is important because alcohol is not the only possible cause of these symptoms.
What Is Alcohol-Related Brain Damage?
Alcohol-related brain damage is an umbrella term for cognitive and neurological problems linked to long-term heavy alcohol use and related complications. It can include memory and executive-function problems, Wernicke-Korsakoff syndrome, vascular injury, traumatic brain injury, and damage associated with repeated withdrawal. It is broader than one single diagnosis.
Some diseases caused by alcohol, especially severe liver disease, can also affect thinking through complications such as hepatic encephalopathy. ARBD may develop much earlier than common progressive dementias; the Alzheimer’s Society notes that people diagnosed with ARBD are often between about 40 and 60. Doctors therefore consider drinking history, nutrition, medical problems, neurological findings, and daily functioning when assessing possible brain injury.
How Alcohol Can Damage the Brain
The effects of alcohol on the brain can develop through several overlapping processes rather than one single pathway. Long-term heavy drinking can alter brain structure and communication, including systems involved in memory, judgment, attention, and coordination. Poor nutrition and reduced thiamine absorption can deprive brain cells of vitamin B1, which is essential for normal energy metabolism.
Research also links chronic alcohol exposure with neuroinflammation and oxidative stress. Alcohol can increase stroke risk, contribute to liver problems that affect brain function, and raise the chance of head injuries. Repeated withdrawal may place further stress on the nervous system. Which mechanisms matter most depends on drinking patterns, nutritional status, withdrawal history, and other medical conditions.
Alcohol-Related Dementia vs. Wernicke-Korsakoff Syndrome
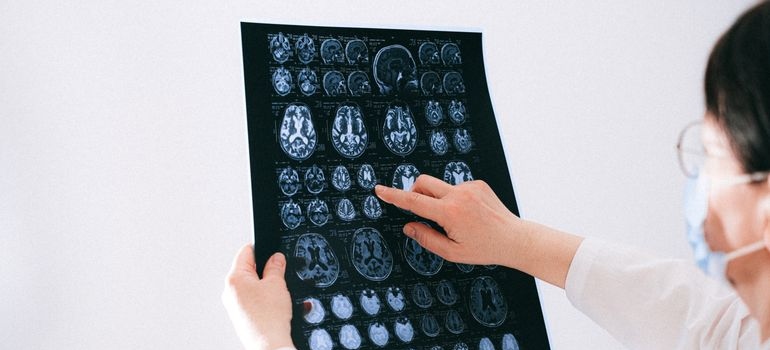
The broader condition is distinct from Wernicke-Korsakoff syndrome, sometimes informally called wet brain. Alcohol-related cognitive impairment can result from several types of brain injury associated with prolonged heavy drinking. Wernicke encephalopathy is an acute condition caused by severe thiamine deficiency, while Korsakoff syndrome is a chronic memory disorder that may follow untreated or undertreated Wernicke encephalopathy. These conditions can overlap, but they should not be used as interchangeable diagnoses.
What Is Wernicke Encephalopathy?
Wernicke encephalopathy is an acute neurological emergency caused by severe thiamine, or vitamin B1, deficiency. Long-term heavy alcohol use raises the risk because it can reduce food intake and interfere with the body’s ability to absorb thiamine. Symptoms may include confusion, serious balance problems, abnormal eye movements, double vision, drowsiness, or reduced responsiveness.
You should not wait for confusion, eye problems, and poor coordination to appear together. A medical review in The BMJ notes that the full classic group of three symptoms appears in only about 10% of cases. Prompt treatment with parenteral thiamine can prevent further injury and reduce the risk of Korsakoff syndrome, disability, or death.
What Is Korsakoff Syndrome?
Korsakoff syndrome is a chronic disorder marked mainly by severe memory impairment, usually linked to thiamine deficiency and often following untreated or undertreated Wernicke encephalopathy. A person may struggle to form new memories or recall past events. Some people fill gaps in memory with inaccurate information without intending to deceive; doctors call this confabulation. Planning, organization, decision-making, motivation, and insight may also be affected.
Unlike acute Wernicke encephalopathy, Korsakoff syndrome can leave permanent neurological damage. NIAAA notes that some recovery may occur over many months with abstinence, proper nutrition, and treatment of nutritional deficiencies. However, severe cases may require long-term support or supervised care because memory and daily functioning may remain significantly impaired.

When Wernicke Encephalopathy Requires Emergency Care
Suspected Wernicke encephalopathy needs urgent medical assessment and thiamine treatment, usually in a hospital. Do not wait for every classic symptom to appear. Seek emergency care when someone with heavy alcohol use or severe malnutrition develops signs such as:
- Sudden confusion or mental-status changes: New disorientation, unusual behavior, or difficulty staying alert can signal acute brain dysfunction.
- Severe balance or coordination problems: New trouble standing, walking, or controlling movement may reflect neurological injury.
- Abnormal eye or vision symptoms: Rapid eye movements, double vision, drooping eyelids, or misaligned eyes need prompt assessment.
- Marked drowsiness or reduced responsiveness: Extreme sleepiness, low responsiveness, collapse, or coma requires immediate emergency care.
Symptoms of Alcohol-Related Brain Damage
Symptoms vary with the type and severity of injury, and one sign alone does not prove someone has ARBD. A personality change when drinking alcohol may reflect temporary intoxication rather than lasting damage. More persistent problems that deserve medical assessment include:
- Memory problems: Trouble recalling recent events or learning new information can interfere with normal daily routines.
- Executive-function problems: Planning, organizing, solving problems, and making decisions may become increasingly difficult.
- Reduced attention: A person may struggle to concentrate, follow conversations, or complete tasks with several steps.
- Confusion or poor orientation: They may lose track of time, place, or what is happening around them.
- Neurological changes: Poor balance, coordination problems, reduced insight, or confabulation may occur in some forms of ARBD.

How Alcohol-Related Dementia Differs From Other Dementias
ARBD can resemble Alzheimer’s disease or vascular dementia because all may affect memory, judgment, and everyday independence. The course, however, can be different. Alzheimer’s disease is progressive, while some alcohol-related cognitive impairment may stabilize or improve when alcohol use stops and nutritional or medical problems receive treatment. That does not mean recovery is guaranteed.
Severe thiamine-related damage, stroke, head injury, or other neurological injury can leave lasting deficits. A person can also have more than one condition, including ARBD alongside Alzheimer’s or vascular disease. Doctors therefore consider the pattern and timing of symptoms, drinking and medical history, neurological findings, and changes after stabilization rather than assuming alcohol explains every cognitive problem.
How Doctors Diagnose Alcohol-Related Cognitive Impairment
Doctors cannot diagnose alcohol-related cognitive impairment with one blood test or brain scan. They combine medical and drinking history with cognitive and neurological assessment while ruling out other causes. Evaluation often becomes clearer after intoxication and acute withdrawal have resolved:
- History and daily function: Clinicians ask about drinking, nutrition, symptoms, medications, falls, and changes in independence.
- Cognitive testing: Memory, attention, planning, judgment, and other thinking skills may be checked.
- Neurological examination: Coordination, gait, reflexes, eye movements, and other neurological signs can provide important clues.
- Laboratory and imaging tests: Blood tests and, when appropriate, CT or MRI can help identify other possible causes.
- Follow-up: Repeating assessment after stabilization or abstinence can show whether cognitive problems persist or improve.
Other Conditions That Can Cause Similar Symptoms
Memory loss, confusion, poor judgment, or unusual behavior in someone who drinks heavily does not automatically mean ARBD. Intoxication can temporarily impair memory and decision-making, while withdrawal can cause anxiety, tremor, seizures, or severe confusion. Delirium tremens is a dangerous form of alcohol withdrawal and needs urgent medical treatment.
Doctors may also consider depression, medication effects, head injury, stroke, infection, vitamin deficiencies, and liver-related encephalopathy. Alzheimer’s disease, vascular dementia, and other neurological disorders can occur in people who drink as well. Because several conditions may overlap, the timing of symptoms matters. Medical assessment helps separate temporary alcohol effects from withdrawal, nutritional injury, progressive dementia, or another treatable medical cause.
Can Alcohol-Related Dementia Be Reversed?
Some alcohol-related cognitive changes can improve, but no clinician can promise full recovery. Improvement depends on what caused the damage, how severe it is, how quickly treatment begins, and whether alcohol use stops. Brain functions affected by prolonged heavy drinking may improve over months of abstinence as the brain adapts and recovers. Thiamine replacement and nutritional rehabilitation are particularly important when deficiency is involved.
Wernicke encephalopathy can respond substantially to prompt treatment, although some symptoms may remain. Korsakoff syndrome is more likely to cause persistent or permanent memory deficits. Stroke, severe head injury, or advanced neurological injury may also limit recovery. Treatment therefore focuses on correcting reversible problems quickly while preventing further alcohol-related damage.
How Long Can Cognitive Recovery Take?
Recovery does not follow one fixed schedule. A 2024 systematic review of 16 longitudinal studies involving 783 adults with alcohol use disorder found that many areas of attention, executive function, perception, and memory reached normal-range performance within about 6 to 12 months of abstinence. Some abilities improved earlier, while visual long-term memory could take longer.
These findings are encouraging, but they do not predict recovery for someone with severe ARBD or Korsakoff syndrome. Current clinical guidance notes that the greatest cognitive improvement often occurs during the first three months, while some people continue improving for up to three years. Recovery depends on the type of injury, nutrition, age, other medical conditions, and continued abstinence.

Treatment for Alcohol-Related Brain Damage
Treatment needs to match the cause of the brain injury. Medical care, thiamine replacement, safe withdrawal management, nutrition, and rehabilitation may all be needed. Approaches such as DBT for alcohol use disorder may support behavioral recovery, but they do not repair damaged brain tissue. Addiction treatment matters because reducing or stopping alcohol use can prevent further harm and support neurological recovery.
Medical and Nutritional Treatment
Medical treatment focuses first on problems that can worsen brain injury or become life-threatening. The exact plan depends on symptoms, nutritional status, withdrawal risk, liver health, and whether Wernicke encephalopathy or another acute medical condition is suspected.
- Treat suspected Wernicke encephalopathy urgently: Parenteral thiamine should be given promptly in a medical setting when clinicians suspect it.
- Correct nutritional problems: Care may include thiamine and treatment of other vitamin, electrolyte, hydration, or calorie deficiencies.
- Manage withdrawal safely: Physical dependence may require monitored withdrawal treatment to reduce seizures, delirium, and other complications.
- Treat other medical causes: Liver disease, infection, stroke, head injury, and metabolic problems need their own assessment and treatment.
Cognitive Rehabilitation and Ongoing Support
Cognitive rehabilitation helps a person work around problems with memory, planning, attention, and daily tasks. It does not reverse every form of brain injury, but it can improve function and independence. Care may include memory aids, repeated practice, simple routines, occupational therapy, and strategies for organizing medications, appointments, meals, and finances.
Current clinical guidance recommends multidisciplinary rehabilitation adapted to the person’s level of cognitive impairment, with regular reassessment as recovery continues. Family or carers can provide useful information because someone with executive-function problems may underestimate their difficulties. Severe or permanent impairment may require supervised living, home support, or long-term care. The goal is safer and more independent daily functioning wherever possible.

Treatment for Alcohol Use Disorder
Treating alcohol use disorder is important because continued heavy drinking can add further alcohol-related dementia. A CBT treatment plan for substance abuse may help someone identify drinking triggers, change unhelpful patterns, and develop practical coping skills. NIAAA also supports motivational approaches, mindfulness-based care, contingency management, and family or couples therapy.
Three medications are FDA-approved for alcohol use disorder: naltrexone, acamprosate, and disulfiram. Treatment may need to be simplified or adapted when memory and executive-function problems make complex instructions difficult to follow. Behavioral therapy treats drinking patterns and related mental-health needs; it does not directly reverse neurological injury. Medical, neurological, and addiction teams may need to coordinate care when cognitive impairment is significant.
When to Seek Medical Help
Seek medical care if you or someone close to you develops ongoing memory loss, confusion, poor judgment, balance problems, or difficulty managing normal tasks after long-term heavy drinking. Sudden confusion, abnormal eye movements, severe trouble walking, seizures, or reduced responsiveness need emergency evaluation. Do not suddenly stop heavy daily alcohol use without medical advice if physical dependence may be present, because withdrawal can become dangerous.
A clinician can assess nutritional problems, withdrawal risk, liver disease, head injury, stroke, and other causes of alcohol-related dementia. If ongoing alcohol use also needs treatment, an alcohol rehab Pennsylvania program may be part of longer-term care, but urgent medical or neurological problems should always be evaluated first.
Take Action Before Symptoms Get Worse
Alcohol-related dementia can affect memory, judgment, focus, and daily life, but the outcome is not the same for everyone. Some changes may improve after drinking stops and medical treatment begins, especially when nutrition and thiamine deficiency are addressed early. Other problems, including severe memory damage linked to Korsakoff syndrome, may last much longer or become permanent. That is why new or worsening cognitive symptoms should never be ignored. A medical evaluation can help identify the cause and rule out other conditions. If alcohol use is also causing problems, treatment can help reduce further harm and support recovery. If you are concerned about yourself or someone close to you, reach out for professional help today.
References:
National Institute on Alcohol Abuse and Alcoholism. (n.d.). Wernicke-Korsakoff syndrome. NIAAA Wernicke-Korsakoff resource
National Institute on Alcohol Abuse and Alcoholism. (n.d.). Alcohol and the brain: An overview. NIAAA brain resource
Department of Health and Social Care. (2026). Clinical guidelines for alcohol treatment: People with alcohol related brain damage. 2026 clinical ARBD guidance
Powell, A., Sumnall, H., Smith, J., Kuiper, R., & Montgomery, C. (2024). Recovery of neuropsychological function following abstinence from alcohol in adults diagnosed with an alcohol use disorder: Systematic review of longitudinal studies. Systematic review
Alzheimer’s Society. (n.d.). Alcohol-related brain damage (ARBD): What is it and who gets it? Alzheimer’s Society ARBD resource
Alzheimer’s Society. (n.d.). Treatment and support for ARBD. ARBD treatment and rehabilitation resource
Frequently Asked Questions
Is alcohol-related dementia the same as Korsakoff syndrome?
No. Alcohol-related brain damage (ARBD), sometimes called alcohol-related dementia, is a broader term for cognitive problems linked to prolonged heavy alcohol use. Korsakoff syndrome is a specific, severe disorder commonly associated with thiamine deficiency and often develops after untreated or inadequately treated Wernicke encephalopathy.
Can memory improve after someone stops drinking?
Yes, memory and other thinking abilities may improve after alcohol use stops, particularly when treatment, nutrition, and rehabilitation are provided. NIAAA reports that some alcohol-related brain changes can partially improve with abstinence. However, recovery varies, and severe damage such as Korsakoff syndrome may leave lasting memory problems.
How do doctors tell alcohol-related brain damage from Alzheimer’s disease?
There is no single test. Doctors consider drinking history, symptoms, physical examination, cognitive testing, and often brain imaging while ruling out other causes. Assessment is more reliable after several weeks without alcohol. Unlike Alzheimer’s disease, ARBD may stabilize or improve with abstinence and treatment rather than progressively worsen.
Can someone have Wernicke encephalopathy without all three classic symptoms?
Yes. A person does not need to show confusion, abnormal eye movements, and coordination problems at the same time. Some people with Wernicke encephalopathy have only one or two recognizable symptoms. Because it is a medical emergency, suspected symptoms require urgent evaluation and thiamine treatment.
How long can cognitive recovery take after stopping alcohol?
Recovery varies widely. Some people with alcohol-related brain damage improve within several months, while others may need years of rehabilitation before reaching their highest level of independence. NIAAA also notes that recovery from Korsakoff syndrome, when it occurs, may continue over many months with abstinence and nutritional treatment.
Can alcohol-related brain damage become permanent?
Yes. Some alcohol-related cognitive impairment can improve, but severe or prolonged damage may be permanent. Untreated Wernicke encephalopathy can progress to Korsakoff syndrome, which can cause profound and sometimes irreversible memory impairment. Prompt thiamine treatment, abstinence, adequate nutrition, and medical care can reduce the risk of further damage.
Admissions
Family Programs
“5-star treatment
experience”
Every element of this treatment experience is 5-star: one-on-one counseling, group therapy, Adventure Trek, lodging, amenities, food, staff. Inpatient and outpatient services are the best you’ll find anywhere. Staff truly care for each individual and want to see them succeed in their recovery. A very special place. Love LC from the bottom of my heart
Meg Boyle |


Take the First Step Towards a Healthier Life
Begin Today













